A missed appointment isn't just an empty slot on the schedule. It’s clinician time that can’t be recovered, staff effort that produced no care, and a patient who may now be further from diagnosis, treatment, or follow-up.
The useful shift is this: no-shows are not random. They usually come from a small set of operational failures that practices can identify and fix. In an MGMA Stat poll on patient no-shows in 2025 (265 responses, August 2025), 60% of medical practices said their no-show rates stayed the same compared with 2024, 13% said they decreased and 27% said they increased. Practices that held or reduced their rates most often credited consistent patient communication: frequent digital reminders, automated calls, and occasional live outreach, along with easy cancellation options.
That matters because it reframes how to reduce patient no shows. The answer is rarely a single reminder text. The practices that make progress usually combine scheduling access, clear cancellation rules, easy rescheduling, and a multi-channel reminder process that reaches patients the way they respond.
The True Cost of an Empty Chair
One no-show rarely stays contained to one no-show.
A new patient misses an intake. The provider loses a high-value slot. The front desk has a gap they can’t fill on short notice. A referral source waits longer for feedback. The patient often doesn’t disappear either. They call back later, usually needing another prime appointment time, which pushes someone else further out.
That’s the operational cost. The clinical cost can be worse.
When patients miss follow-up visits, medication checks, prep-dependent procedures, or chronic care reviews, practices don’t just lose productivity. They lose continuity. Staff then spend time chasing the patient, documenting outreach, re-verifying coverage, and rebuilding a visit that should have happened the first time.
The mistake many practices make is treating no-shows as a patient discipline issue. Some no-shows are about forgetfulness, but many come from friction the practice created without meaning to. Long lead times, confusing instructions, weak reminder workflows, hard-to-reach scheduling teams, and cancellation processes that feel like work all push patients toward silence instead of communication.
Practical rule: If a patient can’t confirm, ask a question, or reschedule in under a minute, your reminder process is incomplete.
The good news is that most no-show reduction work is operational, not mysterious. Practices that improve usually do a few basic things consistently. They shorten the time between booking and visit. They make reminders conversational instead of one-way. They stop relying on one channel. And they remove avoidable barriers before the appointment becomes a missed appointment.
That’s where the return sits. Not in punishing absence after the fact, but in designing a system that makes attendance easier than disappearing.
What the Research Says About Reducing No-Shows
No-show research is broad: systematic reviews cover dozens of studies across specialties and countries. The findings below are the ones a practice can act on. Settings and study designs differ, so treat them as direction and measure your own baseline before and after each change.
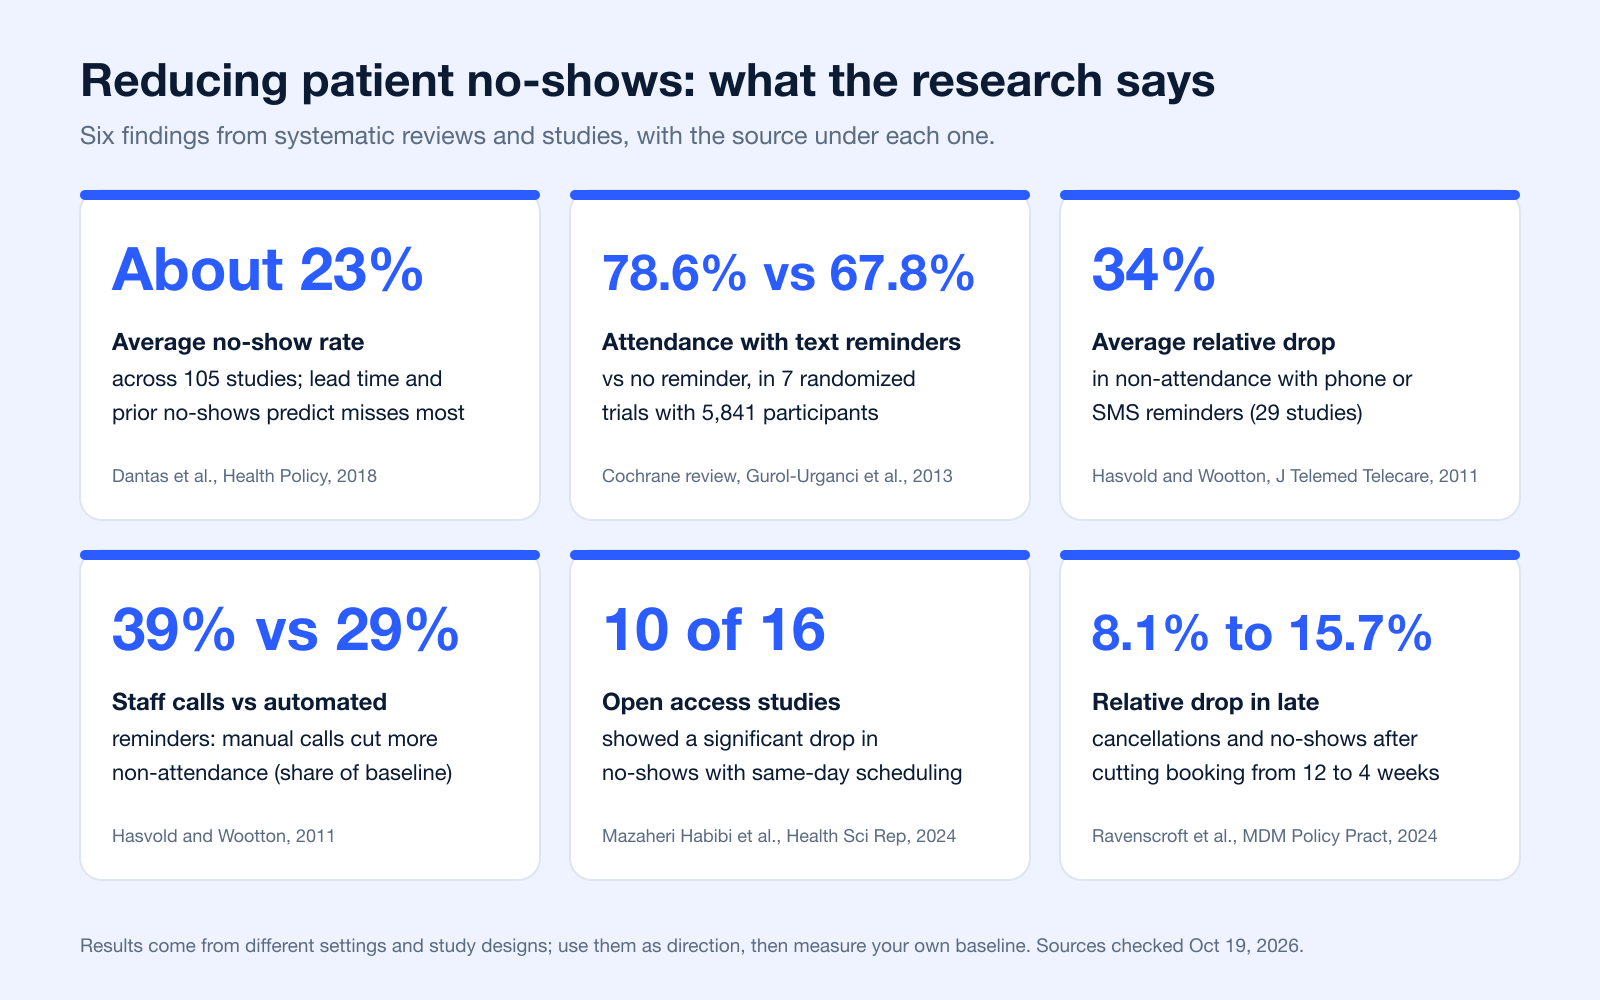
| Finding | Result | What it means for a practice | Source |
|---|---|---|---|
| Average no-show rate | About 23% across 105 studies; 13.2% in Oceania to 43.0% in Africa | Benchmark your own rate; long lead times and prior no-shows were the most reported predictors | Dantas et al., 2018 |
| Text reminders vs no reminder | Attendance 78.6% vs 67.8% (7 randomized trials, 5,841 participants) | Send at least one text reminder to every patient who agreed to texts | Cochrane review, 2013 |
| Phone and SMS reminders | Non-attendance fell by an average of 34% of the baseline rate (29 studies); no difference between a reminder the day before and the week before | Sending a reminder matters more than the exact day | Hasvold and Wootton, 2011 |
| Staff calls vs automated reminders | Manual calls cut non-attendance by 39% of baseline, automated reminders by 29% | Automate for everyone; save staff calls for high-risk visits | Hasvold and Wootton, 2011 |
| Reminders aimed at high-risk patients | Phone calls to patients a model flagged as likely to miss: median risk ratio 0.61 (3 trials); texts: 0.91 (1 trial) | Use no-show history to decide who gets the extra call | Oikonomidi et al., 2023 |
| Same-day (open access) scheduling | 10 of 16 studies found a significant drop in no-show rates | Hold some same-day capacity | Mazaheri Habibi et al., 2024 |
| Shorter booking horizon | Cutting the horizon from 12 to 4 weeks: 8.1% to 15.7% relative drop in last-minute cancellations and no-shows (one pediatric organization, 73,482 visits) | Pull long-booked follow-ups closer | Ravenscroft et al., 2024 |
| Cost | Cost per attendance was 55% and 65% lower with text reminders than with phone call reminders (2 studies) | Lead with text, escalate to calls for non-responders | Cochrane review, 2013 |
Two patterns run through the research. Lead time keeps showing up as a predictor of missed visits, and reminders work best as a sequence rather than a single message. The rest of this guide turns those findings into policies, reminder workflows, and metrics.
First Look Inward Understanding Your No-Show Problem
Practices with high no-show rates rarely have one attendance problem. They usually have three or four smaller problems hiding inside the schedule.
That is why the first job is diagnosis. Pull the data from your EHR or practice management system and identify where missed appointments cluster. In real practices, the pattern often shows up around new patient visits, prep-heavy procedures, long-booked follow-ups, Monday mornings, or one provider whose schedule runs further out than everyone else.
A no-show problem has a shape. If you miss that shape, you end up sending the same text reminder to every patient and wondering why results stay flat.
Start with a baseline everyone uses
Use one formula and stick to it: (no-shows / total appointments) x 100.
That sounds basic, but teams often derail here. Front desk may count only true no-shows. Operations may include late cancellations that could not be refilled. Billing may look at something else entirely. If each department is tracking a different numerator, no one can tell whether the problem is getting better or worse.
For context, a systematic review of 105 studies put the average no-show rate at about 23%, and a health plan tip sheet for providers cites a range of 5% to 55% (Dantas et al.; Central California Alliance for Health). Your own baseline matters more than either number.
Pull at least these views:
- By appointment type: New patient, follow-up, annual wellness, imaging, procedure, therapy, behavioral health
- By provider: Schedule structure, patient mix, and visit length often change attendance rates
- By day and time: Early morning, lunch-adjacent, and late-day slots often perform differently
- By lead time: The gap between booking and visit date matters more than many practices expect
- By payer and geography: This can surface transport barriers, cost concerns, or poor phone access
- By outreach result: Confirmed, delivered with no response, failed delivery, cancelled, rescheduled
That last field is where many practices find the operational gap.
Look for causes you can fix
Counts matter, but patterns matter more. A schedule full of misses six weeks out calls for a different response than a schedule full of missed colonoscopy consults or behavioral health follow-ups.
Use a simple pattern review like this:
| Pattern you see | Likely cause |
|---|---|
| More misses on visits booked far in advance | Long lead time, lower urgency, higher life disruption risk |
| More misses on prep-heavy visits | Instructions unclear, anxiety, or prep not understood |
| More misses in specific neighborhoods | Transportation friction or inconsistent phone service |
| More misses among certain patient groups | Communication channel mismatch |
| More misses after eligibility or estimate discussions | Financial hesitation |
Channel strategy transitions from theoretical to practical. If text messages are delivered but older patients respond to voice, or if mobile numbers are outdated in a rural population, an SMS-only workflow leaves money on the table. Practices usually do better with a HIPAA-safe reminder system that can mix text, email, live-call escalation, ringless voicemail, and voice broadcasting based on patient behavior. This guide to HIPAA-compliant appointment reminder workflows covers the communication side in more detail.
Audit the patient journey like an operator
Review the process step by step, from scheduling to appointment time.
Ask direct questions:
- Can the patient confirm, cancel, or reschedule without waiting on hold?
- Do reminders include the exact date, time, location, and prep instructions in plain language?
- Are you sending reminders early enough for a patient to arrange transportation, time off, or childcare?
- Do you know which patients ignore text but answer a phone call or voicemail drop?
- Does your staff have rules for when silence triggers live outreach?
Weakness in any of those steps creates avoidable misses. The reminder may have gone out. The patient still may not have had a usable path to respond.
It also helps to review your attendance policy against a written external model, such as the Did Not Attend policy of Insight Diagnostics, a UK clinic. The value is not copying another clinic word for word. The value is seeing whether your own process clearly defines reminders, patient responsibility, documentation, follow-up, and escalation after repeated absences.
One more point often gets missed. Contact data quality is part of no-show analysis. If numbers are outdated, consent records are incomplete, or patients were never asked for their preferred channel, your communication performance report will look better than the patient experience. Delivery is not the same as reach.
The practices that reduce no-shows fastest are usually the ones that stop treating every empty chair as the same event. They identify which appointments are at risk, which patients need a different channel, and where staff workflow is creating friction. That is how a vague attendance problem becomes a set of fixable operational issues.
Build a No-Show Resistant Foundation with Smart Policies
Practices that cut no-shows usually fix access and policy before they add more reminders. If the appointment is booked too far out, the cancellation path is clumsy, or staff apply rules inconsistently, missed visits stay high no matter how many texts go out.
A no-show resistant schedule starts with fewer opportunities for patients to fall off the calendar. That means shorter lead times, clear attendance expectations, and booking rules based on actual demand patterns.
Shorten the runway
Long booking windows create failure points. Transportation changes. Work schedules shift. Symptoms improve. Patients forget why they booked in the first place.
A 2024 systematic review of open access scheduling (16 studies, mostly before-and-after comparisons) found that 10 reported a significant drop in no-show rates after clinics expanded same-day access. A pediatric outpatient organization in Ontario that cut its booking horizon from 12 weeks to 4 saw last-minute cancellations and no-shows fall by an estimated 8.1% to 15.7% in relative terms (Ravenscroft et al.). The operational lesson is straightforward. The longer the gap between booking and visit, the more likely life gets in the way.
Start by reviewing how many appointments sit weeks out that could be handled sooner. Follow-ups are often the easiest place to intervene. In primary care and many specialty groups, holding back some same-day or next-day capacity improves attendance without adding staff.
A few scheduling changes usually produce the fastest return:
- Hold same-day capacity for predictable late demand
- Review the backlog every week and pull forward appropriate visits
- Track third-next-available appointment to spot access strain
- Adjust slot templates to real demand instead of historical habit
Make cancellation and rescheduling easy
A policy fails when the patient understands it but cannot act on it.
This pattern is common. The practice asks for 24 hours' notice, but the only way to cancel is to call during office hours, wait on hold, and hope someone answers. Patients who hit that friction late in the day often do nothing. The result is a silent no-show that could have become a refillable opening.
Easy rescheduling should be built into the policy itself. Patients need a clear way to confirm, cancel, or request a new time without starting from zero. That is one reason multi-channel outreach works better than SMS alone. Some patients will tap a text link. Others will respond to a call, a voicemail drop, or a live outreach attempt after they miss earlier messages.
A good attendance policy is easy to read, easy for staff to explain, and easy for patients to follow.
Whatever model you start from, put the rules in writing and make them sound fair rather than hostile: what the practice will do, what the patient needs to do, and how to reach someone when plans change.
Use agreements carefully
Patient agreements can help in the right cases. They are most useful for repeat no-show patients, high-demand consults, imaging, procedures, and any visit where prep time or reserved resources create real cost.
The wording matters. A blunt agreement can damage trust and increase friction at the front desk. A clear agreement sets mutual expectations. It explains what the practice will do, what the patient needs to do, and what happens after repeated missed appointments.
Useful elements often include:
- A stated cancellation window
- A documented process for repeated no-shows
- Special handling for prep-dependent visits
- Rebooking rules for patients with chronic attendance issues
Staff need a script, not just a form. If each scheduler explains the policy differently, enforcement gets uneven and patients push back.
Overbook with discipline
Overbooking should be precise. Broad double-booking is usually a sign that the schedule template is masking a deeper access problem.
Use your own history to identify where no-shows cluster by provider, appointment type, day of week, or time of day. Then test limited overbooking only in those segments. A cardiology group might find that low-acuity follow-ups on Friday afternoons have enough fallout to justify one extra slot. A surgical clinic with long room times and prep requirements usually cannot absorb that risk without creating delays.
The trade-off is simple. An empty chair wastes capacity. A full waiting room burns patient goodwill and staff time.
A practical rule is to overbook only where your data supports it and where the provider can absorb variation without running behind all session.
Put financial policy in its proper place
Fees, deposits, and card-on-file policies can reduce avoidable misses, but they should be used selectively. They work better for high-demand specialties, procedure-based care, and patients with repeated no-shows than they do for routine visits where price sensitivity is high.
Practices need to weigh deterrence against access. A strict no-show fee may improve attendance in one segment while causing other patients to avoid booking at all. That is a poor trade if the practice serves cost-sensitive populations or relies on long-term continuity.
If you use fees or deposits, keep the policy operationally clean:
- Disclose the rule before booking
- Train staff on exceptions and hardship cases
- Offer a fast rescheduling path instead of forcing the patient to disappear
- Document the reason whenever the fee is waived
If you see Medicare patients, CMS allows physicians and suppliers to charge Medicare beneficiaries for missed appointments as long as the same policy applies to non-Medicare patients; CMS treats the fee as a charge for "a missed business opportunity", not for a service (Medicare Claims Processing Manual, chapter 1, section 30.3.13). Medicaid programs and commercial payer contracts can set their own rules, so check them before charging. This is general information, not legal or billing advice.
Communication and policy have to match. If patients can confirm by text but cannot cancel except by phone, staff will still lose appointments they could have saved. Practices building those workflows can use this HIPAA-compliant appointment reminder guide as an operational reference for aligning consent, channel rules, and response handling.
Good policy reduces friction before the reminder sequence begins. That gives your multi-channel outreach a better chance to fill the slot instead of documenting the miss.
Automate Communication with a Multi-Channel Reminder Engine
Most reminder systems fail for one reason. They assume one message on one channel is enough.
It usually isn’t.
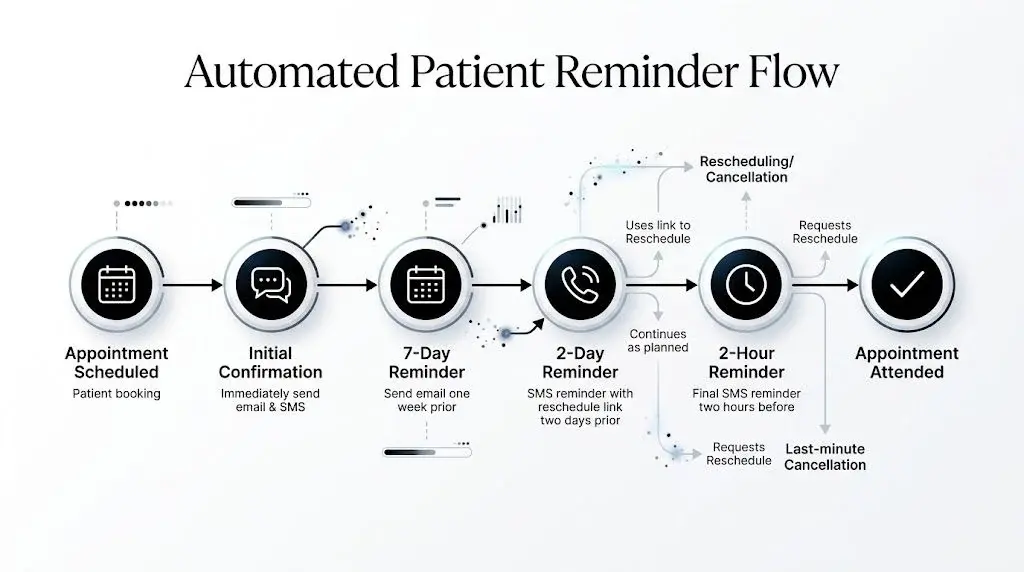
A patient may ignore texts at work, miss phone calls from unknown numbers, and never check email. Another may prefer a call because they’re older, rural, or less comfortable with portals and links. A strong system doesn’t force one behavior. It uses SMS, voice broadcasting, and ringless voicemail together, with two-way response options and clear pathways to confirm or reschedule.
The research supports this layered approach. A systematic review of 29 studies found that phone and SMS reminders cut non-attendance by an average of 34% of the baseline rate (Hasvold and Wootton), and a Cochrane review found that text reminders raised attendance from 67.8% to 78.6% compared with no reminder (Cochrane review). Practices in the MGMA poll that held or cut their no-show rates also pointed to easy cancellation options, not just reminders. That is the point many teams miss. One-way reminders notify. Two-way reminders solve problems before the slot is lost.
Build the sequence before you write the messages
The sequence matters as much as the wording.
Each touchpoint should have a job. One confirms the appointment exists. Another gives enough notice to rearrange life. Another captures late friction and prompts action. If there’s still silence, the system should escalate the channel or route the patient to staff.
Here’s a practical framework.
| Timing | Channel | Message Content / Goal |
|---|---|---|
| At booking | SMS or email | Confirm date, time, location, and next step. Catch bad contact info immediately. |
| 7 days before | SMS or voice | Early reminder. Invite confirmation or rescheduling while options still exist. |
| 48 hours before | SMS with two-way reply | Ask patient to confirm, ask a question, or tap to reschedule. |
| 24 hours before | Voice call or ringless voicemail for non-responders | Reach patients who ignore text. Reinforce attendance details and response options. |
| Day of visit | Short SMS | Final prompt with arrival or check-in detail. |
| After missed confirmation | Automated follow-up | Offer reschedule path instead of waiting for a no-show. |
That framework is adaptable. A prep-heavy procedure may need more education earlier. A routine follow-up may need less language and more simplicity.
Two notes on timing. In the Hasvold review, reminders sent the day before and the week before performed about the same, so the exact day matters less than having a sequence. And if you rely on the FCC's healthcare exemption rather than the patient's consent for automated calls and texts to cell phones, it allows one message a day and three a week at most (47 CFR 64.1200(a)(9)(iv)(F)), so trim the sequence for those patients. The rules are covered below.
Use SMS for action, not for decoration
Text is fast, direct, and easy for most patients. But many practices waste it on passive messages.
A better SMS reminder does three things:
- identifies the appointment clearly
- asks for one simple action
- offers a reschedule path immediately
Examples:
SMS example Dr. Lee’s office: You’re scheduled for Tuesday at 10:30 AM. Reply C to confirm or R to reschedule.
SMS example Reminder from Valley Clinic. Your appointment is tomorrow at 2:00 PM. Need to change it? Reply R and we’ll send options.
For more wording, see these appointment confirmation text templates.
The goal isn’t to cram every detail into one message. The goal is to prompt a decision.
If a patient doesn’t respond, that’s useful signal. It tells you who needs a second channel.
Voice still works, especially when text doesn’t
Healthcare teams sometimes treat voice as outdated. That’s a mistake.
Voice remains effective for older patients, patients with lower digital comfort, patients with prep anxiety, and visits where details matter. Automated voice broadcasting is also useful when you need consistency across a large schedule but still want a more human-feeling reminder.
A strong voice reminder includes:
- the patient’s appointment date and time
- the location or provider name
- one clear response option
- a transfer or callback path
If your platform supports AI text-to-speech, staff can standardize messaging without recording fresh audio for every update. If it supports press-1 transfers or similar routing, patients can move directly into a reschedule or question workflow.
When deciding where staff time goes, note that manual staff calls cut more non-attendance than automated reminders in the Hasvold review (39% vs 29% of the baseline rate). A review of predictive targeting found that phone call reminders aimed at patients flagged as high risk reduced no-shows (median risk ratio 0.61 across 3 randomized trials) (Oikonomidi et al.). Automated messages cover the whole schedule; staff calls are best saved for the patients most likely to miss.
Ringless voicemail fills a gap other channels miss
This is the underused channel most practices should at least test.
Ringless voicemail delivers a voice message directly to the patient’s voicemail inbox without requiring a live answer. That makes it useful when patients ignore unknown calls, don’t respond to texts, or prefer listening over reading. It’s particularly practical for elderly patients, low-tech populations, and patients who never engage with links.
The value of ringless voicemail is not novelty. It’s coverage.
A patient may not answer a standard call from a clinic number they don’t recognize. They may not open a text if they’re busy. But they may listen to a voicemail while driving home, during a break, or when reviewing missed messages. For reminder workflows, that creates a useful middle ground between intrusive calling and passive texting.
A simple ringless voicemail script works best:
This is a reminder from Lakeside Medical. You have an appointment on Thursday at 9:00 AM. If you need to reschedule, please call us or use the link sent to your phone. We look forward to seeing you.
Keep it short. Use plain language. Mention the action. Don’t bury the purpose.
For setup basics, see this ringless voicemail getting started guide.
Keep reminders within HIPAA and TCPA rules
Reminders are routine, but two US rule sets still apply to them. Under HIPAA, HHS says providers may communicate with patients about their care and may leave messages, but should "limit the amount of information disclosed", for example "leaving only its name and number and other information necessary to confirm an appointment, or ask the individual to call back" (HHS FAQ 198). Keep diagnoses, test names and treatment details out of texts and voicemails.
Under the TCPA, automated calls and texts need consent. The FCC has said that a patient who gives a phone number to a healthcare provider has given prior express consent for HIPAA-covered healthcare calls within the scope of that consent (FCC 15-72, para. 141). Separately, the FCC's healthcare exemption lets providers send reminders to cell phones when all of its conditions are met, including these (47 CFR 64.1200(a)(9)(iv)):
- Free to the patient and sent only to the wireless number the patient provided
- The provider's name and contact information in every message (at the start of a voice call)
- Limited to purposes such as appointment and exam confirmations and reminders, with no marketing or billing content
- Voice calls generally one minute or less, texts 160 characters or less
- One message a day and three a week at most per patient
- An easy opt-out in every message ("Reply STOP" for texts), honored immediately
Ringless voicemail is a call under these rules: the FCC ruled in 2022 that it needs the same consent as other calls (FCC 22-85). For a fuller walkthrough of HIPAA, business associate agreements and the healthcare exemption, see this guide to health care SMS. This is general information, not legal advice.
Segment before you automate at scale
A reminder engine should not treat every patient the same.
Segment by factors you already have:
- Appointment type
- History of no-shows
- Preferred contact method
- Need for prep instructions
- Distance from clinic
- Language preference
- Whether the patient confirmed previously by text, voice, or portal
For example, a new patient with a history of non-response may get SMS plus voice plus ringless voicemail. A reliable returning patient may only need one two-way text. A rural patient who rarely clicks links may do better with voice and a simple callback option than with SMS alone.
This is also the right point to mention tools. A platform such as Broadcast’s automated appointment reminder workflow can coordinate SMS, voice broadcasting, and ringless voicemail in timed sequences with segmentation, scheduling, merge tags, and analytics. That kind of orchestration is what makes multi-channel practical instead of manual.
To compare dedicated tools, see this roundup of appointment reminder software, or how SMS reminders work in Broadcast.
Fix the common failure points
Even good reminder systems break in predictable ways.
These are the most common:
- Bad contact data: If intake doesn’t validate mobile, landline, and consent details, automation amplifies bad records.
- One-way messaging: Patients read the reminder, realize they can’t make it, and then do nothing because there’s no easy response path.
- Poor timing: A reminder that lands too late creates a no-show. A reminder that lands too early without follow-up gets forgotten.
- No escalation rule: Silence from a high-risk patient should trigger another channel or staff outreach.
- No compliance discipline: Opt-in, preference handling, and documentation matter in healthcare communication.
The reminder that matters most is the one that gives the patient an easier alternative than not showing up.
Write for stressed patients, not internal staff
Reminder copy often sounds like it was written for compliance review instead of human use. Keep messages clear, respectful, and short.
Good reminder language is:
- specific
- plain
- actionable
- free of jargon
Bad reminder language is packed with policy wording, abbreviations, and unnecessary detail.
For prep-dependent appointments, add only the critical instruction and point to the full details elsewhere. For example, remind the patient there is preparation required and how to get help if they’re unsure. If the prep is confusing, people disappear rather than admit they don’t understand.
The strongest reminder engine doesn’t rely on one heroic message. It uses a timed sequence, channel escalation, patient preference, and an easy response path so attendance becomes the simplest option.
Measure Success and Continuously Optimize Your Strategy
A reminder system isn’t finished when it goes live. It’s finished when it produces stable attendance patterns month after month.
The first mistake practices make is tracking only the final no-show rate. That tells you the outcome, but not where the system is breaking. If your no-show rate is unchanged, you need to know whether messages weren’t delivered, weren’t read, weren’t acted on, or reached the wrong patients on the wrong channel.
Track operational KPIs that explain behavior
Watch metrics that show movement before the appointment is lost:
- Confirmation rate: Are patients actively responding?
- Reschedule rate: Are reminders preventing silent no-shows by prompting earlier action?
- Delivery rate by channel: Did the SMS, voice call, or ringless voicemail reach the patient?
- Non-response rate: Which cohorts stay silent even when messages are delivered?
- Lead-time trend: Are long-booked visits still causing the most trouble?
- No-show rate by segment: Provider, visit type, payer, geography, and patient cohort.
That’s where segmentation starts to matter.
Segmenting by risk has research behind it. In a review of predictive model-based interventions, reminders aimed at patients a model flagged as likely to miss reduced no-shows: text reminders with high certainty (median risk ratio 0.91, 1 trial) and phone calls with moderate certainty (median 0.61, 3 trials) (Oikonomidi et al.). Health plans give similar advice in plainer terms: the Central California Alliance for Health tip sheet for reducing patient no-shows suggests reminders 48 hours before and on the day of the visit, calling unconfirmed patients on the day, and noting in the schedule which patients need an extra reminder call.
Optimize one variable at a time
Don’t rewrite your full workflow every month. Change one variable, observe it, and keep what improves patient response.
Test things like:
| Variable | What to test |
|---|---|
| Channel order | SMS first, then voice, versus voice first for older cohorts |
| Message style | Short directive copy versus warmer conversational copy |
| Timing | Earlier reminder for specialty visits versus tighter timing for primary care |
| Response path | Reply keyword, callback number, or direct reschedule link |
| Segment rule | Separate workflows for new patients, procedures, and repeat no-show patients |
This is the same discipline marketers use when improving conversion paths: change one thing, compare it with a similar period or a control group, and keep what works. Small changes compound.
Use reporting to drive staff action
Analytics are only useful if someone owns the next step.
If older patients confirm more often through voice than text, update the preference rule. If one provider’s Friday schedule has chronic non-response, adjust booking patterns. If prep-heavy visits show high non-response at the 48-hour mark, trigger live outreach sooner.
For teams already using campaign dashboards, the same measurement logic applies to reminders. The framework for measuring campaign effectiveness is useful because it pushes teams to connect message delivery, engagement, and outcomes rather than staring at one top-line number.
Better no-show performance usually comes from better segmentation, not louder reminders.
Practices that keep improving don’t assume all patients behave alike. They tighten lead times where possible, learn which channel works for which patient, and treat every non-response pattern as a clue rather than a dead end.
Frequently Asked Questions About Reducing Patient No-Shows
Should every practice charge a no-show fee?
No. A fee can help in the right context, but it shouldn’t be the first tool you reach for.
For high-demand consults, expensive prep, or repeat offenders, a fee or deposit may be reasonable if the rule is clear and consistently explained in advance. For general care, using fees as the main strategy often backfires. Patients who are already anxious about cost may avoid rescheduling and disappear. In most practices, access, communication, and reminder design produce cleaner results than punishment alone.
What should we do with chronically absent patients?
Treat chronic no-shows as a workflow segment, not just a behavior problem.
Give them a tighter scheduling model. Offer same-day or short-lead appointments where possible. Use stronger confirmation rules. Route them into a higher-touch reminder sequence. If the patient repeatedly misses despite support, then apply a documented attendance policy and rebooking conditions. The goal is to protect capacity without making staff negotiate the rules from scratch every time.
Are text reminders enough?
Often, no.
Text works well for many patients, but not all of them. Some patients don’t respond to links, some ignore unknown messages, and some are much more likely to listen than read. That’s why practices trying to learn how to reduce patient no shows effectively should think in layers, not channels. SMS is one layer. Voice is another. Easy rescheduling is another. Staff escalation for high-risk visits is another.
Where does ringless voicemail fit?
Ringless voicemail is useful when patients ignore texts or don’t answer calls, but still listen to voicemail messages later. Two rules apply. Under HIPAA, keep the message minimal: HHS suggests leaving only the practice name and number and what is needed to confirm the appointment, or asking the patient to call back (HHS FAQ 198). Under the TCPA, the FCC ruled in 2022 that ringless voicemail is a call, so it needs the same consent as other calls (FCC 22-85).
That makes it practical for:
- Older patient populations
- Patients who rarely click SMS links
- Rural or low-tech populations
- Second-touch reminders after no text response
- Prep-sensitive appointments where hearing a human-style message matters
It’s not a replacement for SMS. It’s a complementary channel that fills a gap.
How much should we personalize reminders?
More than most practices do now.
At minimum, personalize by appointment type, patient preference, language, and no-show risk. A routine follow-up doesn’t need the same sequence as a new patient consult or a procedure with prep. Patients with transport or financial barriers may need more than a reminder. They may need earlier outreach, a chance to reschedule easily, or staff intervention before the day of service.
What usually fails even when a practice thinks it has a good system?
Three things.
First, the data is wrong. Old phone numbers and weak intake validation will sink automation fast. Second, the reminder is one-way, so patients who need help have no simple next step. Third, the sequence stops at “message sent” rather than “patient responded.” Good systems don’t just send reminders. They create movement toward confirmation, cancellation, or rescheduling.
What is a normal patient no-show rate?
It varies widely by specialty, population and country. A systematic review of 105 studies found an average of about 23%, from 13.2% in Oceania to 43.0% in Africa (Dantas et al.). Calculate your own rate with one formula, (no-shows / total appointments) x 100, and track it by visit type and lead time.
When should appointment reminders be sent?
Use a sequence rather than one message. In a review of 29 studies, reminders sent the day before and the week before reduced non-attendance by similar amounts (Hasvold and Wootton). A common pattern is a confirmation at booking, a reminder about 48 hours before with a way to reply, and a short message on the day, with a call for patients who have not confirmed.
Do automated reminder calls work as well as staff calls?
Both help, but staff calls did more in the research. Manual calls cut non-attendance by 39% of the baseline rate and automated reminders by 29% (Hasvold and Wootton). Text reminders also cost less per attendance than phone call reminders in the Cochrane review, so many practices automate for everyone and reserve staff calls for high-risk visits.
How do you reduce no-shows for referrals and new patients?
New appointments carry more risk: in one safety-net surgical clinic study, new appointments independently predicted higher no-show rates (Braschi et al.). Book referrals as soon as possible, confirm the appointment and the contact number at booking, explain any preparation in plain language, and add a call for patients who do not confirm.
Can you charge Medicare patients for missed appointments?
Yes, under CMS policy, as long as the missed appointment policy applies equally to Medicare and non-Medicare patients (Medicare Claims Processing Manual, chapter 1, section 30.3.13). Check Medicaid and commercial payer rules separately. This is general information, not legal or billing advice.
If your practice wants a practical way to run HIPAA-compliant reminders across SMS, voice broadcasting, and ringless voicemail without stitching together manual workflows, Broadcast gives teams a way to build timed sequences, segment patients, and automate confirmations and rescheduling outreach across the channels patients respond to.